
 Indonesia denies foreign claim to rescued orangutans
 Turkey hosts COP31 climate talks in Antalya.
 Pope meets Argentine bishops.
 APOD: 2026 November 8 – Major Fireball Meteor
 Indonesian Horror Hit ‘Pabrik Gula’ Gets 2028 Sequel as MD Entertainment Lines Up Three Imax Films
Are coronary stents necessary?
Are coronary stents necessary? - AI News Breaking
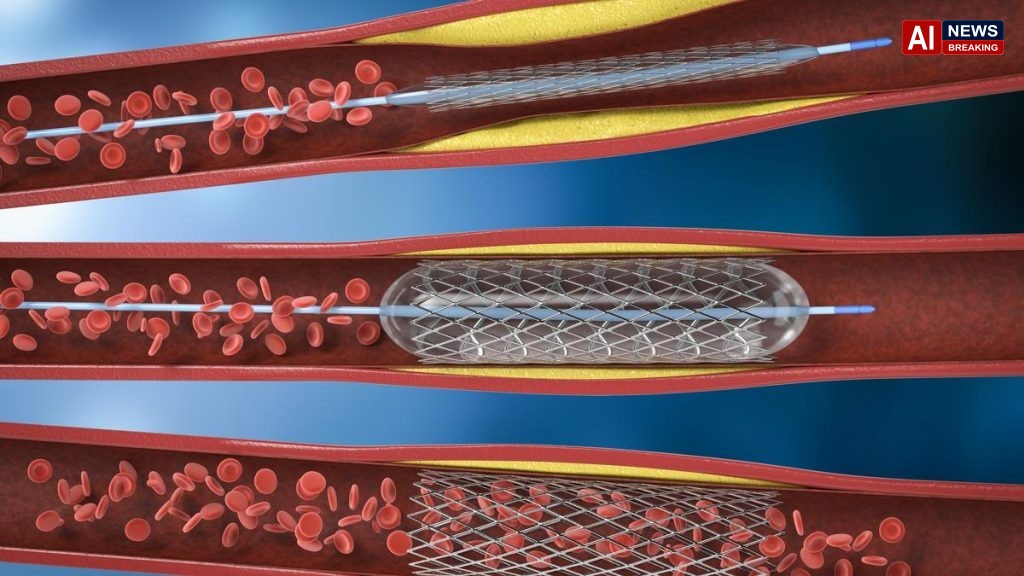
Are coronary stents necessary? Coronary artery disease remains the leading cause of death worldwide, and its management has evolved dramatically over the past few decades. At the heart of contemporary treatment lies the use of stents, tiny mesh tubes inserted into narrowed arteries to restore blood flow..
Yet, the question of whether stenting is always necessary has sparked debate among clinicians, patients, and policymakers alike. This article examines the evidence, explores alternative therapies, and considers the broader implications for healthcare systems and individual patients. The primary indication for stenting is a significant narrowing—or stenosis—of a coronary artery, typically detected during an angiogram..
When a blockage reduces blood flow below a critical threshold, the risk of myocardial infarction or sudden cardiac death rises sharply. In such scenarios, stents act as a life‑saving intervention, maintaining vessel patency and preventing catastrophic events. For many patients, the immediate benefit of stenting is clear: the artery is mechanically dilated, the plaque is compressed, and blood can travel more freely to the heart muscle..
However, not every angiographic finding warrants an invasive procedure. Minor or moderate stenoses may not pose an acute threat and can often be managed with lifestyle modifications, medication, and regular monitoring. In these cases, the risks of stenting—such as bleeding, infection, or the rare but serious complication of restenosis—may outweigh the benefits..
Thus, clinicians must weigh the severity of the narrowing against the potential for adverse outcomes before recommending stenting. Current guidelines from major cardiovascular societies emphasise a patient‑centred approach. The American College of Cardiology and the European Society of Cardiology both recommend that decisions about stenting should incorporate functional assessments, such as fractional flow reserve or instantaneous wave‑free ratio, alongside anatomical imaging..
These tests help determine whether a narrowed segment is truly flow‑restricting and likely to cause symptoms. When functional significance is confirmed, stenting becomes more clearly justified. Beyond the clinical decision, the cost implications of widespread stent use are substantial..
Stents, particularly drug‑eluting varieties that release medication to prevent restenosis, can be expensive. When multiplied across the millions of patients who undergo angiography each year, the cumulative expense becomes a significant burden on national health budgets and insurance systems. Consequently, health economists and policymakers are increasingly scrutinising the cost‑effectiveness of routine stenting, especially for lesions that are borderline in severity..
Alternatives to stenting have gained traction in recent years. Optimal medical therapy, comprising antiplatelet agents, statins, beta‑blockers, and ACE inhibitors, can stabilize plaques and reduce the risk of future events. In some patients with stable disease, aggressive medical management has been shown to be as effective as percutaneous coronary intervention (PCI) in preventing death and myocardial infarction..
Moreover, surgical revascularisation, such as coronary artery bypass grafting, may be preferred for multivessel disease or complex lesions where stenting is less effective. Patient preferences also play a pivotal role. Some patients may prioritise the less invasive nature of PCI over surgery, valuing the quicker recovery time and fewer hospitalisations associated with stenting..
Others may be wary of the potential need for prolonged dual antiplatelet therapy, which carries its own bleeding risks. Shared decision‑making, supported by clear communication of risks, benefits, and alternatives, is essential to align treatment with individual values and expectations. Recent trials have shed light on the long‑term outcomes of stenting versus medical therapy..
The ISCHEMIA trial, for instance, followed patients with stable ischemic heart disease for over five years and found no significant difference in death or non‑fatal myocardial infarction between those managed medically and those receiving early invasive therapy, including stenting. These findings suggest that, in selected populations, a conservative approach may be as safe as an interventional one. Nevertheless, the story is not uniform across all patient groups..
In individuals with acute coronary syndromes, such as unstable angina or ST‑segment elevation myocardial infarction, timely stenting is unequivocally life‑saving. Prompt revascularisation can restore perfusion, limit myocardial damage, and improve survival. In these urgent contexts, the window of opportunity for stenting is narrow, and the decision is often straightforward..
Technological advances continue to refine the stenting process. Newer-generation drug‑eluting stents boast thinner struts, improved drug formulations, and better biocompatibility, all of which reduce the incidence of restenosis and stent thrombosis. Additionally, bioresorbable stents—designed to dissolve after healing—are under investigation and may offer long‑term vessel preservation without permanent foreign material..
However, these innovations also bring additional costs and require rigorous evaluation before they can be widely adopted. Public perception of stenting is shaped by dramatic medical narratives and high‑profile cases. Media coverage often focuses on the dramatic rescue of patients with visible heart attacks, reinforcing the idea that stents are a universal cure..
Yet, the nuanced reality is that many coronary lesions are asymptomatic, stable, and manageable without intervention. Education campaigns that explain the spectrum of coronary disease and the criteria for stenting could help patients make informed choices and reduce unnecessary procedures. In summary, coronary stenting is undeniably a cornerstone of modern cardiovascular care, providing rapid, effective relief for patients with severe, flow‑limiting coronary artery disease..
However, its necessity is not absolute; many patients with mild to moderate stenoses can achieve equivalent outcomes through optimal medical therapy alone. The decision to stent should therefore be guided by a combination of anatomical severity, functional significance, patient preference, and cost‑effectiveness considerations. As evidence continues to accumulate and technology advances, clinicians will be better equipped to tailor interventions to each patient’s unique clinical.
Updated: October 27, 2026
This development highlights evolving dynamics and may have broader implications in the near term.







